
What Are Variable Decelerations During Labor?
During active labor and delivery, healthcare teams continuously assess the fetus using electronic fetal monitoring (EFM). This monitoring produces a visual strip displaying both uterine contractions and the baby’s baseline heart rate. Observing how the fetal heart rate responds to the mechanical stress of contractions helps clinicians determine whether the baby is receiving sufficient oxygen.
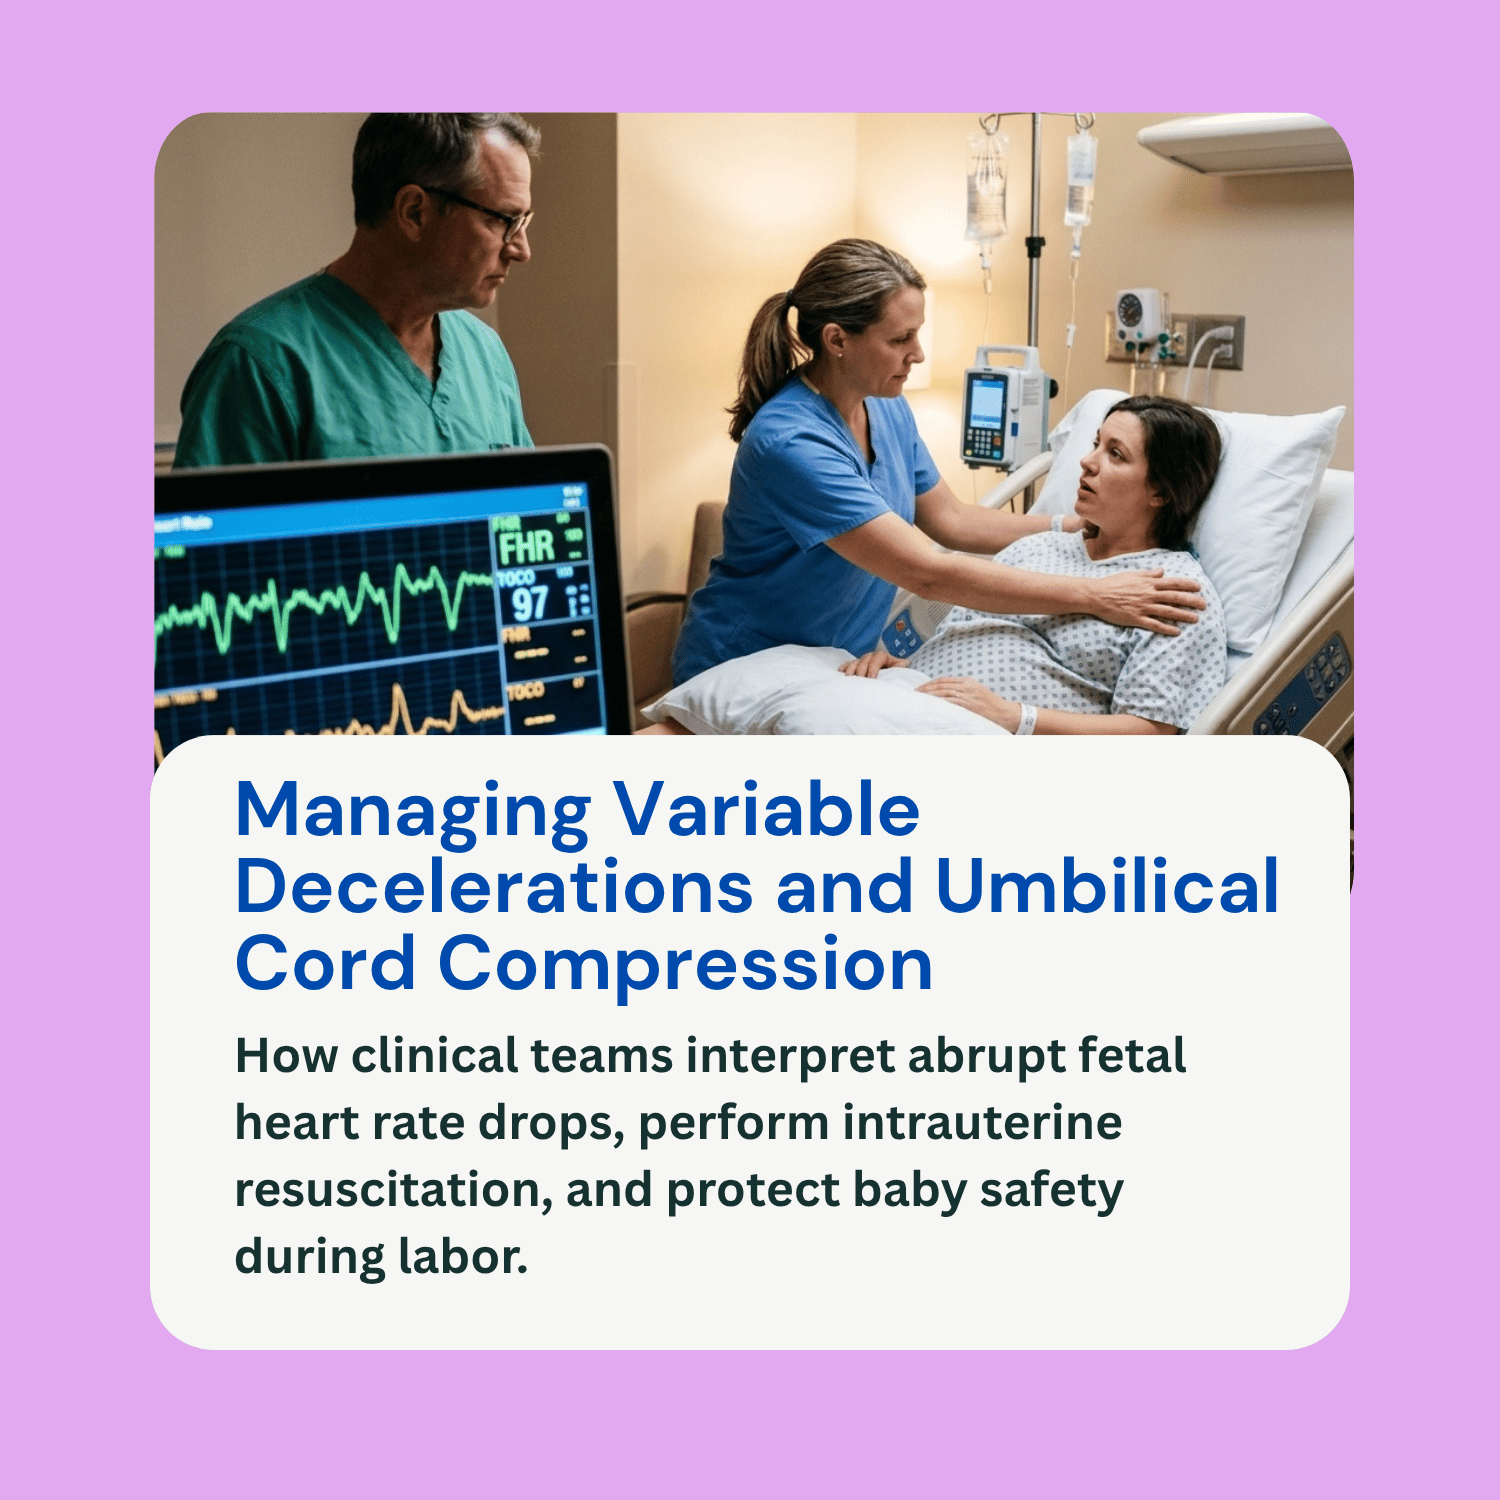
One of the most frequently observed patterns on a monitoring strip is variable decelerations fetal heart rate drops. A variable deceleration is defined as an abrupt, visually distinct decrease in fetal heart rate where the time from the beginning of the drop to the lowest point (nadir) is less than 30 seconds. The heart rate must drop by at least 15 beats per minute below baseline and last for at least 15 seconds, but less than 2 minutes from start to return. Unlike other deceleration patterns, variables differ widely in shape, depth, duration, and timing relative to uterine contractions. This guide explains the mechanisms behind variable decelerations, how they contrast with other patterns, how clinical teams evaluate their severity, and why swift management matters.
Contrasting Variable, Early, and Late Decelerations
To ensure accurate interpretation of fetal monitoring strips, clinicians distinguish variable decelerations from early and late patterns based on timing, shape, and underlying physiology:
Early Decelerations: These feature a gradual, smooth decrease in fetal heart rate that mirrors the onset and peak of a uterine contraction. The lowest point of the heart rate drop aligns directly with the peak of the contraction. Early decelerations are caused by head compression during labor, which stimulates the vagus nerve. They are considered a normal physical response and do not indicate oxygen deprivation.
Late Decelerations: These are smooth, gradual drops in heart rate where the decline begins after a contraction has already started, reaching its lowest point after the contraction’s peak. Late decelerations reflect reduced blood flow through the placenta (uteroplacental insufficiency) and signal fetal hypoxia, requiring immediate evaluation.
Variable Decelerations: These are marked by an abrupt, sharp decrease in heart rate, often taking on a characteristic “V,” “U,” or “W” shape on the monitoring printout. Their relationship to contractions is unpredictable—they may occur before, during, or between contractions. The primary mechanism driving variable decelerations is umbilical cord compression.
Umbilical Cord Compression and Fetal Response
The umbilical cord carries oxygenated blood from the placenta to the fetus via one umbilical vein and returns deoxygenated blood via two umbilical arteries. During labor, contractions or fetal movement can temporarily press the umbilical cord against the baby’s body or the uterine wall.
The initial phase of umbilical cord compression squeezes the thin-walled umbilical vein first, briefly reducing blood flow back to the baby’s heart. This causes a transient rise in fetal heart rate known as a “shoulder.” As the compression tightens during the peak of a contraction, the thicker umbilical arteries become occluded. This creates a sudden increase in fetal systemic blood pressure. Baroreceptors in the baby’s circulatory system detect this high pressure and send rapid neural signals via the vagus nerve to slow down the heart rate, causing the abrupt vertical drop seen on the monitor. Once the contraction eases and cord compression releases, systemic blood pressure normalizes, and the heart rate returns to baseline, often accompanied by a secondary recovery “shoulder.”
Evaluating Severity and Duration
While occasional, mild variable decelerations are common and generally well-tolerated by a healthy fetus, persistent or severe variable patterns require active clinical assessment:
Mild to Moderate Variable Decelerations: These involve heart rate drops that remain above 70 beats per minute and resolve within 60 seconds. When accompanied by moderate baseline variability (normal fluctuation in heart rate), mild variables indicate that the fetus is successfully compensating for brief interruptions in cord blood flow.
Severe or Recurrent Variable Decelerations: A variable deceleration is classified as severe when the heart rate drops below 70 beats per minute and lasts longer than 60 seconds. When severe variable decelerations recur with more than 50% of contractions over a 20-minute period, the fetus exhausts its oxygen reserves.
Loss of Baseline Variability: The most critical factor when evaluating variable decelerations is the presence of baseline variability. Moderate variability indicates a healthy, well-oxygenated central nervous system. However, if recurrent variable decelerations are accompanied by minimal or absent variability—or if the heart rate takes progressively longer to return to baseline (delayed return)—it signals progressive fetal hypoxia and metabolic acidosis.
Clinical Management and Resuscitation Protocols
When electronic monitoring displays severe or recurrent variable decelerations, the medical team initiates a structured series of intrauterine resuscitation maneuvers to relieve cord pressure and optimize fetal blood flow:
Maternal Position Changes: The first and most effective step is repositioning the mother. Turning the mother onto her left or right side, or placing her in a knee-chest or Trendelenburg position, shifts the weight of the fetus away from the umbilical cord, releasing physical compression.
Intravenous Fluid Administration: Providing a rapid infusion of intravenous fluids expands maternal blood volume and increases placental blood flow.
Discontinuing Uterine Stimulants: If labor-inducing medications such as oxytocin (Pitocin) are being administered, nurses immediately reduce or stop the infusion to decrease contraction frequency and give the umbilical cord time to decompress.
Amnioinfusion: In cases where low amniotic fluid (oligohydramnios) or repetitive cord compression is present, clinicians may perform an amnioinfusion. This involves instilling warm sterile saline solution into the uterine cavity through an intrauterine pressure catheter to cushion the umbilical cord.
Supplemental Oxygen and Delivery Planning: Administering supplemental oxygen to the mother may be used if maternal hypoxemia is present. If intrauterine resuscitation fails to resolve severe variable decelerations, or if the fetal heart rate trace degrades to a Category III pattern showing absent variability, an expedited delivery via operative vaginal delivery or emergency C-section is required.
Frequently Asked Questions (FAQ)
Are variable decelerations always dangerous for the baby?
No. Occasional or mild variable decelerations with normal baseline variability are very common in labor and rarely cause long-term harm. They become dangerous only when they are deep, prolonged, recurrent, or paired with a loss of baseline heart rate variability.
What is the main cause of variable decelerations?
The primary cause of variable decelerations is physical compression of the umbilical cord during contractions. Common factors include a nuchal cord (cord wrapped around the neck), low amniotic fluid levels, cord entanglement, or cord prolapse.
How does an amnioinfusion help with variable decelerations?
An amnioinfusion adds fluid back into the amniotic sac. This extra fluid acts as a liquid cushion around the umbilical cord, preventing uterine contractions from squeezing the cord tightly against the fetus or uterine wall.
Can unmanaged variable decelerations cause a birth injury?
Yes. If severe, recurrent variable decelerations are left unmanaged and resuscitation attempts fail, prolonged lack of blood flow can cause fetal asphyxia, metabolic acidosis, Hypoxic-Ischemic Encephalopathy (HIE), and permanent neurological injury.