
What Is a Category III Fetal Heart Rate Tracing?
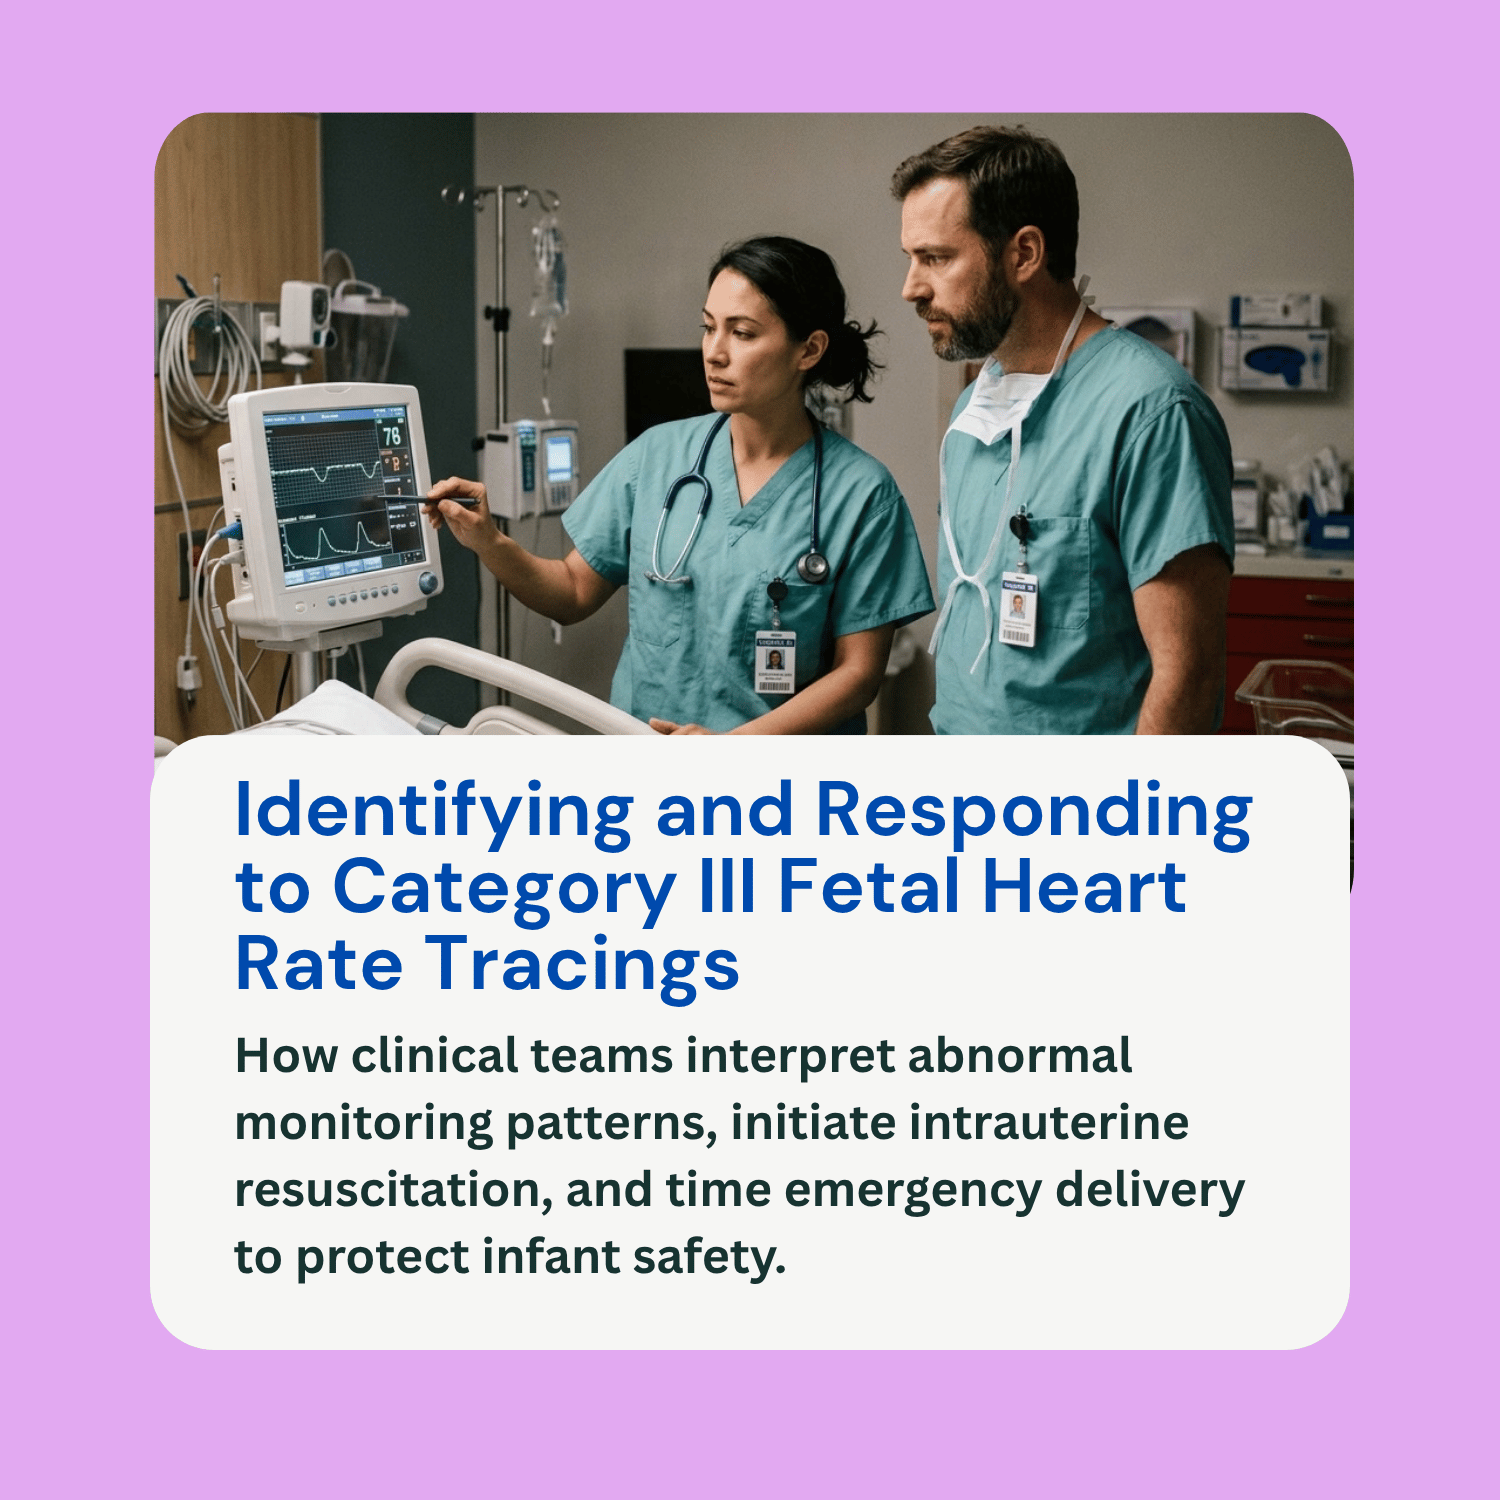
Continuous electronic fetal monitoring (EFM) is a standard tool used during labor and delivery to monitor the baby’s heart rate in relation to maternal uterine contractions. The visual readout, known as a fetal heart rate tracing, provides real-time information regarding fetal oxygenation and nervous system stability.
To help clinical teams quickly assess risk and take appropriate action, the American College of Obstetricians and Gynecologists (ACOG) established a standardized three-tier classification system for fetal heart rate tracings. While Category I represents a normal, reassuring pattern and Category II encompasses indeterminate traces requiring continued monitoring, a Category III fetal heart rate tracing represents an abnormal, high-risk pattern. A Category III designation indicates that the fetus is at significant risk of acidemia and hypoxia, demanding urgent, coordinated clinical intervention. This educational guide explains the criteria for a Category III tracing, standard resuscitation protocols, and why the duration of the abnormal pattern matters.
Understanding the Fetal Heart Rate Tier System
Obstetric teams evaluate electronic fetal monitoring strips by looking at baseline rate, baseline variability, accelerations, and decelerations. Tracings are categorized into one of three distinct tiers:
Category I (Normal): Indicates normal acid-base status. The baseline heart rate is between 110 and 160 beats per minute, baseline variability is moderate, late or variable decelerations are absent, and early decelerations or accelerations may be present.
Category II (Indeterminate): Includes a wide range of patterns that are not explicitly Category I or Category III. Examples include baseline tachycardia, minimal variability, or recurrent variable decelerations with moderate variability. Category II tracings require continued observation, evaluation, and reevaluation.
Category III (Abnormal): Indicates abnormal fetal acid-base status at the time of observation. These tracings signal progressive fetal oxygen deprivation and require immediate evaluation and intrauterine resuscitation.
Defining Characteristics of a Category III Tracing
To be formally classified as Category III, a fetal heart rate tracing must exhibit specific, severe abnormal features. A tracing is Category III if it displays either of the following two primary conditions:
Absent Baseline Variability with Recurrent Late Decelerations, Recurrent Variable Decelerations, or Bradycardia: Baseline variability reflects the normal, healthy interplay between the sympathetic and parasympathetic nervous systems. When variability is completely absent (a flat line on the heart rate trace), it signals significant nervous system depression. If absent variability is paired with recurrent late decelerations (slowing after contractions), recurrent variable decelerations (abrupt drops from cord compression), or sustained bradycardia (a baseline rate below 110 beats per minute), the tracing is classified as Category III.
Sinusoidal Pattern: A sinusoidal pattern is a distinct, smooth, undulating sine-wave-like baseline pattern that recurs regularly over a period of 20 minutes or longer. Unlike variable decelerations, a sinusoidal trace is smooth and uniform, reflecting severe fetal anemia, massive fetomaternal hemorrhage, or acute profound hypoxia.
Immediate Intrauterine Resuscitation Protocols
When a fetal monitoring strip transitions into a Category III pattern, the medical team initiates immediate, standardized bedside actions aimed at restoring fetal blood flow and oxygenation:
Maternal Position Changes: The mother is placed on her left or right side, or moved into a knee-chest position, to relieve pressure off the inferior vena cava and lessen potential umbilical cord compression.
Intravenous Fluid Bolus: Administering a rapid bolus of isotonic intravenous fluids increases maternal blood volume, boosting placental perfusion and oxygen delivery to the fetus.
Discontinuing Uterine Stimulants: Any active infusion of oxytocin (Pitocin) or other labor-inducing agents is stopped immediately to decrease contraction frequency and intensity, giving the placenta time to re-oxygenate between contractions.
Maternal Oxygen Administration: If maternal hypoxemia is present or suspected, supplemental oxygen may be administered via a non-rebreather mask to optimize oxygen saturation.
Tocolytic Medication: In cases of uterine hyperstimulation (too many contractions in a short window), clinicians may administer a tocolytic medication to temporarily halt uterine contractions.
Why Duration, Context, and Delivery Timing Matter
A Category III tracing does not automatically mean a birth injury has occurred, but it represents an urgent window where rapid action is critical to prevent permanent damage:
Duration of the Tracing: Fetal brain tissue can tolerate short periods of reduced oxygen, but persistent Category III patterns reflect exhaustion of fetal compensatory mechanisms. The longer a Category III tracing persists without resolution following resuscitation efforts, the greater the risk of severe metabolic acidemia, Hypoxic-Ischemic Encephalopathy (HIE), and permanent neurological injury.
Surrounding Clinical Context: A Category III tracing must be evaluated in the context of the overall labor progress, maternal vital signs, and individual risk factors such as placental abruption, uterine rupture, or active infection (chorioamnionitis).
Decision-to-Delivery Interval: If intrauterine resuscitation fails to improve the fetal heart rate pattern rapidly—or if a sinusoidal pattern is present—guidelines recommend moving swiftly toward expedited delivery via emergency C-section or operative vaginal delivery to minimize oxygen starvation.
Frequently Asked Questions (FAQ)
Does a Category III tracing always mean the baby will have a brain injury?
No. A Category III tracing indicates significant risk of oxygen deprivation, but if the medical team identifies the pattern quickly and either resolves it with resuscitation or delivers the baby promptly, many infants are born without long-term harm.
What is the main difference between Category II and Category III tracings?
Category II tracings are indeterminate and require close monitoring and reassessment, as many can improve or remain stable. Category III tracings are explicitly abnormal and require immediate intrauterine resuscitation and preparation for urgent delivery if improvement does not occur.
What causes a sinusoidal fetal heart rate pattern?
A true sinusoidal pattern is caused by severe fetal anemia, acute severe fetomaternal hemorrhage, umbilical cord occlusion, or severe fetal hypoxia. It is a rare but critical Category III sign that usually necessitates immediate delivery.
How does a Category III tracing factor into medical-legal reviews?
In birth injury reviews, electronic fetal monitoring strips are closely audited. If a Category III pattern was present for an extended period without documented intrauterine resuscitation or a timely decision to perform an emergency C-section, it may indicate a failure to meet the standard of care.