
What Can Placental Pathology Show After a Difficult Birth?
The placenta serves as the essential life-support system for a developing fetus throughout pregnancy and labor, delivering oxygen and nutrients while removing metabolic waste products. Following a complicated labor, emergency C-section, or the delivery of an infant requiring immediate admission to the Neonatal Intensive Care Unit (NICU), obstetricians routinely send the placenta to a pathology laboratory for detailed microscopic evaluation.
For parents seeking answers after an unexpected birth outcome, reviewing a placental pathology difficult birth report can provide vital clues about what occurred during labor or in the weeks leading up to delivery. Pathological examination can identify underlying infections, blood clotting issues, or acute structural disruptions that impacted blood flow to the baby. However, placental pathology alone does not provide a standalone diagnosis of permanent brain injury or prove medical negligence. Instead, it provides objective tissue evidence that must be interpreted alongside continuous electronic fetal heart rate traces, umbilical cord blood gas results, continuous EEG patterns, and neonatal neuroimaging. This educational guide explains why the placenta is examined, common pathological findings, diagnostic limitations, and how results fit into the broader clinical evaluation.
Why the Placenta Is Examined After a Complicated Delivery
While many placentas are discarded after routine deliveries, major professional guidelines from the College of American Pathologists (CAP) and the American College of Obstetricians and Gynecologists (ACOG) recommend formal pathological examination under specific clinical circumstances:
Neonatal Indications: A placenta is submitted for testing whenever a newborn exhibits signs of distress at birth. Key triggers include low 5-minute Apgar scores (below 7), severe umbilical cord arterial acidemia (pH less than 7.00), admission to the NICU, signs of neonatal encephalopathy or Hypoxic-Ischemic Encephalopathy (HIE), early-onset seizures, extreme prematurity, or stillbirth.
Maternal and Intrapartum Indications: Examination is also indicated following maternal complications such as severe preeclampsia, sudden placental abruption, unexplained uterine bleeding, high-grade maternal fever during labor (chorioamnionitis), emergency surgical delivery for non-reassuring fetal heart rate patterns, or structural abnormalities of the umbilical cord.
Common Categories of Placental Pathology Findings
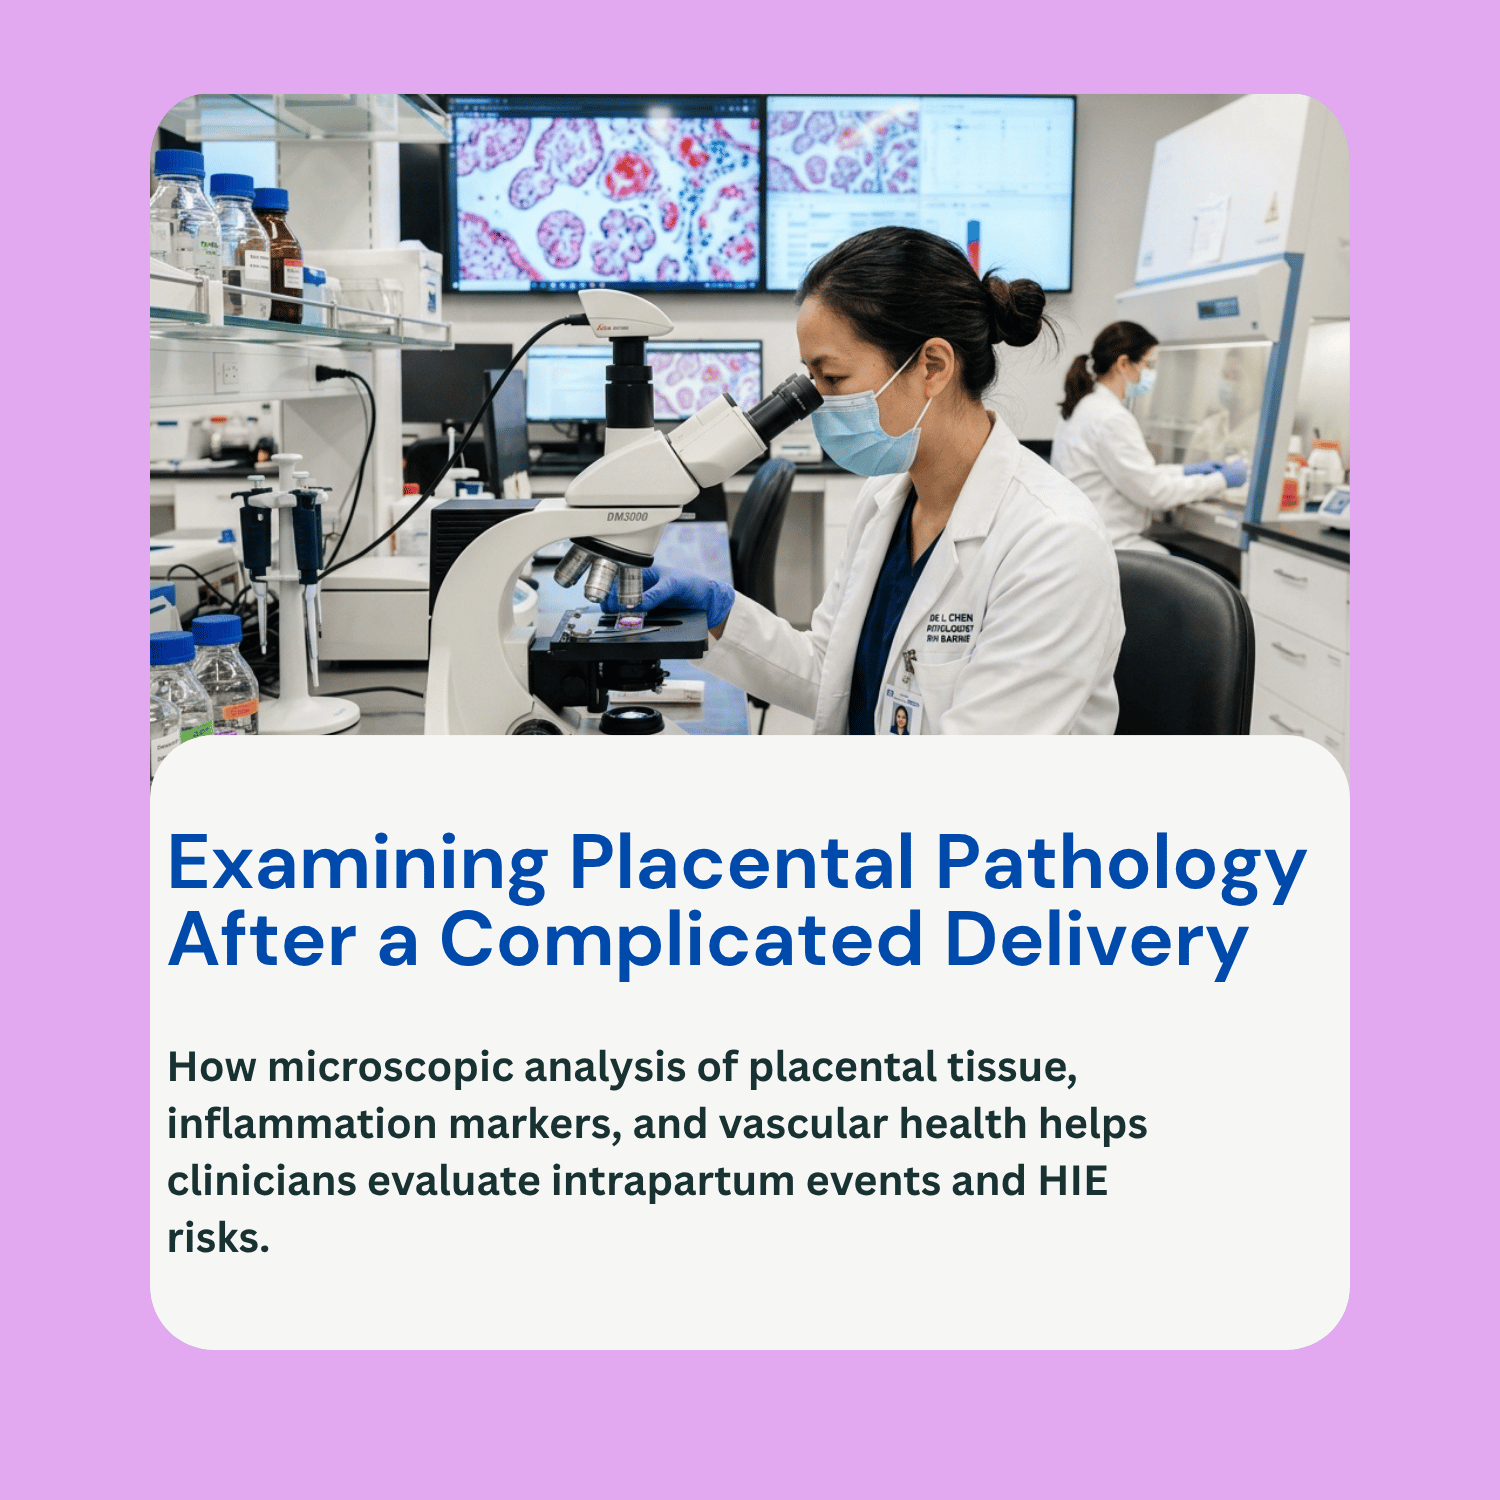
Pathologists conduct both a gross examination (evaluating weight, dimensions, cord insertion, and visible clots) and a microscopic tissue analysis (examining cell structure and blood vessel integrity). Findings typically fall into four primary categories:
Infectious and Inflammatory Patterns (Chorioamnionitis and Fetal Inflammatory Response): Pathologists check for maternal inflammatory responses (chorioamnionitis), where neutrophils infiltrate the fetal membranes, and fetal inflammatory responses (funisitis or chorionic vasculitis), where white blood cells migrate into the umbilical cord vessels. Active infection or systemic inflammation can impair placental blood flow and increase the fetus’s vulnerability to hypoxic brain injury.
Uteroplacental Maternal Vascular Malperfusion (MVM): MVM refers to inadequate arterial blood flow from the mother to the placenta. Pathological markers include accelerated villous maturation, small placental size for gestational age, and multiple placental infarctions (areas of dead tissue caused by lack of blood flow). MVM often develops gradually in conditions like preeclampsia or chronic maternal hypertension, reducing the baby’s metabolic reserves before labor even begins.
Fetal Vascular Malperfusion (FVM): FVM reflects disrupted blood flow within the baby’s side of the placental circulation. Causes include tight cord entanglement, true umbilical cord knots, or hypercoagulable states that lead to blood clots in the fetal chorionic vessels. Microscopic signs include avascular villi and thrombosis, indicating that blood was prevented from circulating properly through the placenta.
Acute Disruption and Hemorrhage (Placental Abruption): In cases of placental abruption, where the placenta prematurely detaches from the uterine wall, the pathologist evaluates the size and age of retroplacental hematomas (blood clots). Large, acute retroplacental clots confirm an abrupt breakdown in maternal-fetal oxygen transfer immediately prior to or during labor.
Understanding Diagnostic Limits: Pathology Alone Cannot Establish Causation
While placental pathology provides invaluable objective data regarding tissue health, medical consensus emphasizes its diagnostic limitations when evaluating birth injuries:
Timing Challenges: Many pathological features—such as chronic maternal vascular malperfusion or small-for-gestational-age villi—develop over weeks or months. Microscopic signs of acute inflammation or cord compression can also develop hours before labor becomes clinically active. Consequently, tissue changes rarely pinpoint the exact minute a neurological injury occurred.
Coexistence with Normal Outcomes: Many placentas exhibit microscopic abnormalities, such as focal inflammation or minor infarctions, without the newborn ever suffering brain damage or long-term complications. The human placenta possesses significant reserve capacity to sustain a baby despite localized tissue damage.
Integrating the Full Medical Record: To determine whether a condition like HIE resulted from intrapartum oxygen starvation, neonatologists and pediatric neurologists must synthesize placental findings with the complete medical timeline. Key factors include whether electronic fetal monitoring strips showed Category III decelerations, whether umbilical arterial cord gases revealed severe metabolic acidemia (pH < 7.00, base deficit $\ge$ 12 mmol/L), and whether subsequent brain MRI scans demonstrated pattern-specific injury in the basal ganglia or watershed regions.
Frequently Asked Questions (FAQ)
How long does it take to get placental pathology results back?
Placental pathology reports typically take anywhere from 3 to 7 business days to complete. The tissue must be fixed in formalin, processed into thin microscopic slides, and thoroughly analyzed by a specialized pathologist.
Can a placental infection cause brain damage even if labor was normal?
Yes. Severe intrauterine infection and inflammation (chorioamnionitis or funisitis) can trigger systemic inflammatory cytokines that cross the blood-brain barrier, making the baby’s brain cells far more vulnerable to injury even during standard labor contractions.
If the placenta shows pathology, does it mean the brain injury was unavoidable?
Not necessarily. While underlying placental pathology (like chronic vascular malperfusion) can reduce a baby’s tolerance for labor, clinical care standards require delivery teams to monitor high-risk pregnancies closely, recognize non-reassuring fetal heart rate patterns promptly, and perform timely interventions or emergency C-sections when fetal distress occurs.
How do placental pathology reports factor into medical malpractice reviews?
Placental pathology provides an objective timeline of pre-existing versus acute factors. Medical and legal experts analyze the report to distinguish whether a brain injury was driven by long-standing antenatal disease or by acute, unmanaged intrapartum events during active labor.